

54-year-old man, a renal transplant recipient (for IgA nephropathy) on immunosuppression, presented with a fluctuant swelling over the medial aspect of the left foot for 6 months.

Radiograph of left foot (AP and lateral)
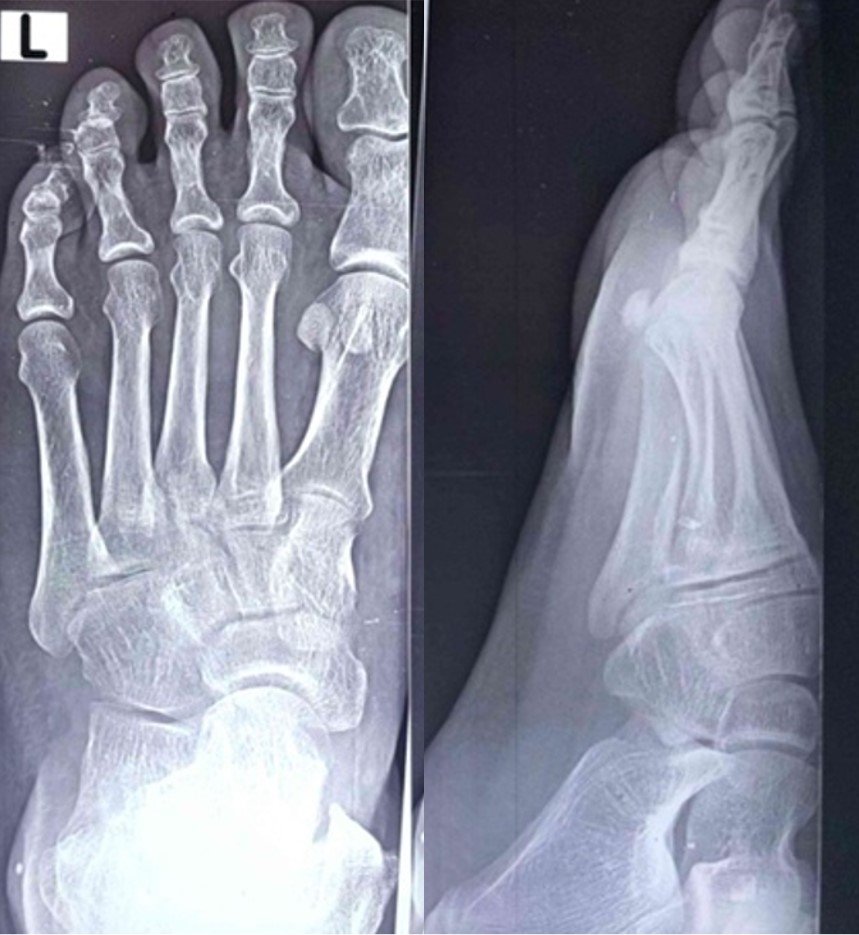
No osteopenia, bony erosion, periosteal reaction or focal lesion. Midfoot joint spaces are preserved
Radiograph was reported as normal
MRI of left foot
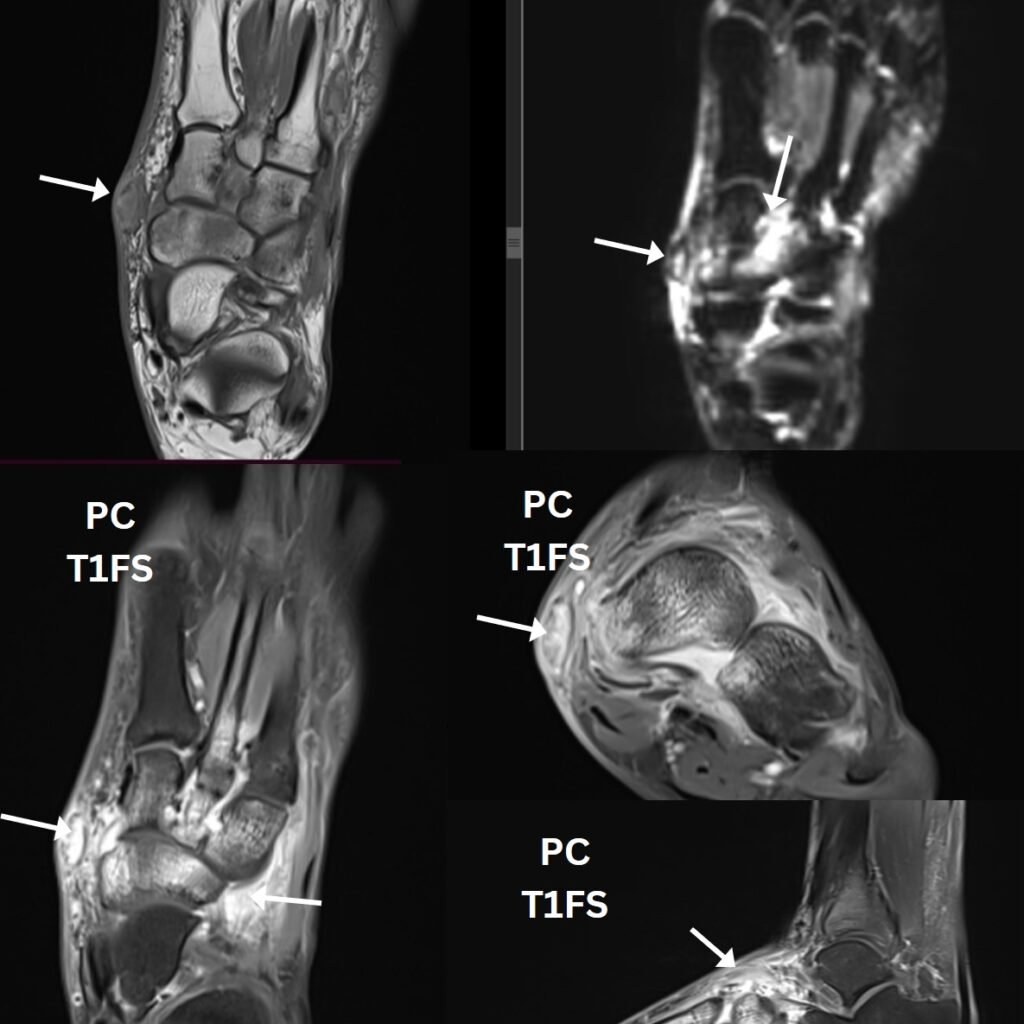
MRI findings
- Oval lesion in the medial subcutaneous plane of the midfoot (arrows): intermediate T1 signal, hyperintense on the fluid-sensitive image. Solid enhancement on post contrast images with thin capsule
- Oedema of the surrounding subcutaneous fat.
- Marrow oedema and enhancement in the adjacent tarsal bones
- Mild intertarsal synovitis.
- Long segment medullary T1 hypointensity and enhancement of 2nd metatarsal shaft.
Radiological Impression
Inflammatory phlegmon with septic intertarsal arthritis and osteomyelitis of 2nd metatarsal.
IMAGING SAYS:
- Subcutaneous phlegmon
- Synovitis of the midfoot
- Marrow oedema and enhancement
PATIENT SAYS:
- Swelling for 6 months
- Painless and non-tender
- No erythema
- Renal transplant recipient on immunosuppression
Wait! These don’t match!!
Florid MRI changes with a quiet clinical picture, in a transplant recipient, should make you think of an opportunistic or indolent organism, or a non-infective mimic.
Differential diagnosis
| Entity | For | Against |
|---|---|---|
| Pyogenic abscess, septic arthritis, osteomyelitis | Commonest; rim-enhancing collection, synovitis, marrow oedema | Usually acute, painful and red; systemic features. Frank osteomyelitis shows confluent T1 marrow replacement |
| Tuberculosis (tenosynovitis, arthritis, osteomyelitis) | Endemic in India; higher risk after transplant; indolent “cold” abscess, midfoot involvement | Non specific imaging, usually more aggressive bone destruction and collections, needs AFB smear, CBNAAT/culture, histology needed |
| Non-tuberculous mycobacteria (e.g. M. haemophilum, M. marinum) | Immunosuppressed host; nodules, tenosynovitis and arthritis of distal limbs | Often multifocal skin nodules; needs mycobacterial culture |
| Nocardiosis | Transplant recipient; subcutaneous abscesses | Usually has lung and brain lesions; branching Gram-positive filaments |
| Eumycetoma (Madura foot) | Foot; painless swelling; endemic in India | Presents as sinuses discharging grains; “dot-in-circle” sign on MRI; grains on US |
| Opportunistic moulds (phaeohyphomycosis, Scedosporium, Fusarium, Aspergillus) | Transplant recipients; indolent subcutaneous cyst or abscess, often on the lower limb | Imaging non-specific; diagnosis needs tissue (stains, culture) |
Non-infective mimics
- Tophaceous gout: Tophi are T1 iso- to hypointense, heterogeneous on T2, variably enhancing, with punched-out erosions with overhanging edges.
- Kaposi sarcoma: has violaceous plaques or nodules on the lower limbs
- Post-transplant lymphoproliferative disorder (PTLD): rarely presents as a soft-tissue mass
- Charcot neuroarthropathy: midfoot-centred, but needs neuropathy (e.g. post-transplant diabetes)
USG guided FNAC of the soft tissue lesion was done
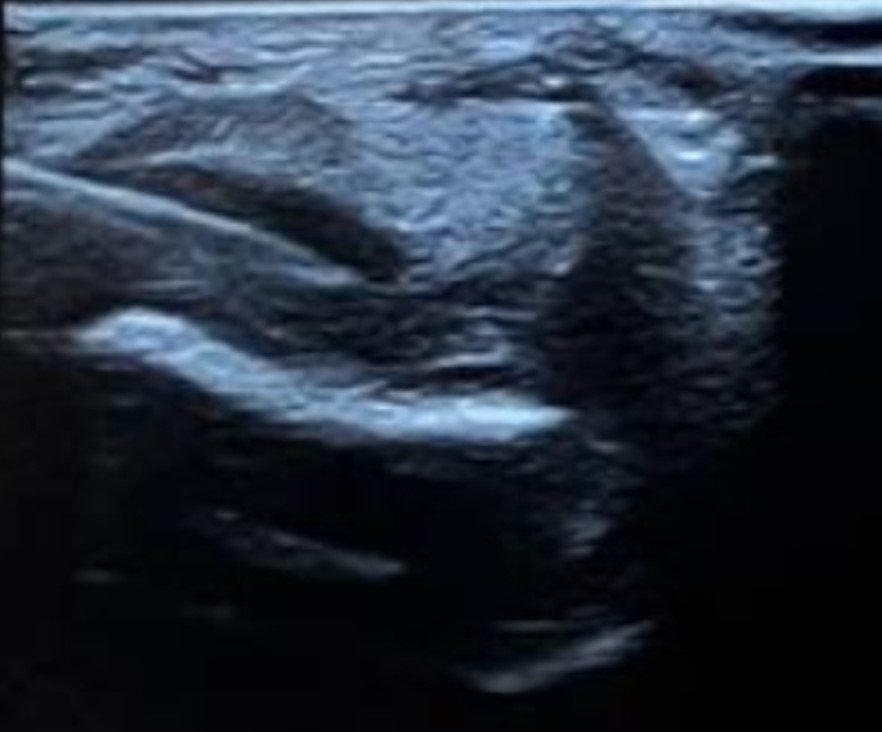
LEARNING POINT: In an immunosuppressed patient, send every aspirate for Gram stain, AFB, KOH/fungal stains and culture, not just cytology. Fungal cultures can be negative, so a tissue diagnosis is needed.
FINAL DIAGNOSIS
PHAEOHYPHOMYCOSIS (DEMATIACEOUS FUNGAL INFECTION) OF THE LEFT MIDFOOT
PHAEOHYPHOMYCOSIS
- Infection by a heterogeneous group of melanised (dematiaceous) fungi, e.g. Alternaria, Exophiala, Cladophialophora, Curvularia
- Melanin in the fungal cell wall is a virulence factor and gives the brown pigment seen in tissue
- Found in soil, plants and wood; enters through minor, often unnoticed trauma (thorns, splinters)
- Spectrum: superficial → cutaneous/subcutaneous (“phaeomycotic cyst”) → deep osteoarticular → disseminated or cerebral disease
- In tissue: pigmented septate hyphae and yeast-like cells, with no grains (unlike mycetoma) and no sclerotic bodies (unlike chromoblastomycosis)
- Risk factors: solid-organ transplant, HIV, neutropenia, autoimmune disease on immunosuppression
LEARNING POINTS
- A near-normal radiograph does not exclude deep infection. Radiographic bone changes lag behind MRI, and indolent (fungal, mycobacterial) infections progress slowly.
- In a transplant recipient, a slowly enlarging, painless, non-inflamed subcutaneous swelling of the foot should raise suspicion of phaeohyphomycosis / other opportunistic infections.
- Clinical–radiological discordance (florid MRI, quiet clinical picture) is the clue.
- Look for discriminators: grains and the dot-in-circle sign (eumycetoma), overhanging-edge erosions and urate on dual-energy CT (gout), and a retained foreign body.